
What keyhole surgery actually changes, how large each advantage really is, when an open operation is still the right call, and the risk figures you are entitled to before you consent.
Reviewed by Dr. Grishma Ranjangaonkar, MBBS, DGO, ICOG Fellowship in Gynecological Endoscopy · Eva WomanCare Clinic, Vashi, Navi Mumbai
Almost all benign gynecological surgery is now done through three or four small cuts rather than one long one, and the advantages are real. They are also frequently oversold, and the recovery is routinely underestimated because people judge it by the size of the dressings. Here is the comparison as we give it in clinic, with the numbers attached.
The short version
Both operations do the same work inside. What changes is how the surgeon gets in and out, and almost every advantage of keyhole surgery follows from that single fact.
Less tissue is cut, so there is less pain, less blood loss, a shorter stay and a faster return to normal life. Current guidance puts it plainly: where an operation can be done laparoscopically and there is no contraindication, it should be.
|
|
Laparoscopy
|
Open surgery
|
|---|---|---|
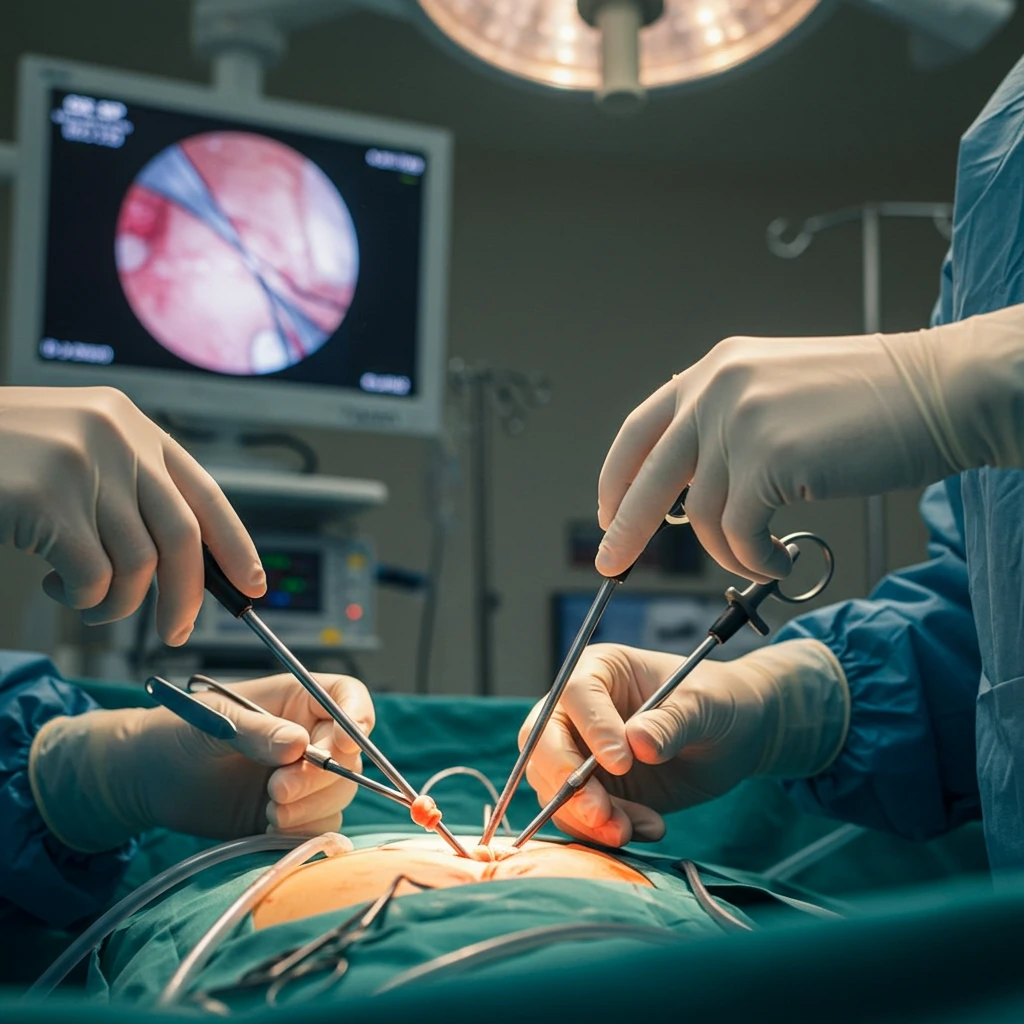
Almost all benign gynecological surgery is now keyhole. These are the operations we do most often at our Vashi clinic.
|
Condition
|
What the operation does
|
Worth knowing
|
|---|---|---|
Keyhole is not automatically better in every situation, and a surgeon who says otherwise is overselling. Open surgery remains the right operation for a very large mass, for dense adhesions from previous surgery, where cancer is suspected, and in some emergencies.
Consent means very little without figures attached. The numbers below are the Royal College of Obstetricians and Gynaecologists consent advice for diagnostic laparoscopy, which is the cleanest published set available. Operative laparoscopy carries the same risks at a somewhat higher rate, because the operation is longer and more is being done.
|
Risk
|
How often
|
What it means
|
|---|---|---|
Recovery after keyhole surgery is faster than after open surgery and slower than the size of the cuts suggests. What you actually had done matters far more than the fact that it was laparoscopic.
Myth
“Small cuts mean a small operation.”
What is actually true
The cuts are small; the operation inside is exactly the same size. A laparoscopic hysterectomy is major surgery performed through keyholes. Judging your recovery by the size of the dressings is the commonest mistake, and it is why the tiredness in week two takes people by surprise.
Myth
“Laparoscopy is only for minor problems.”
What is actually true
It is used for hysterectomy, for deep endometriosis, for ectopic pregnancy and for fibroid removal. The limits are set by the size of what needs to come out and the safety of the anatomy, not by how serious the condition is.
Myth
“Keyhole surgery is more dangerous because the surgeon cannot see properly.”
What is actually true
The view is magnified and, in the deep pelvis, better than the naked eye gets in an open operation. The genuine limitation is the loss of the ability to feel tissue, which is why very large masses and dense adhesions are sometimes better handled open.
Myth
“You can go back to normal in two days because the cuts are tiny.”
What is actually true
You will feel able to long before you should. Nothing heavier than a full kettle for the first week after operative surgery, and no gym, swimming or heavy lifting for four to six weeks.
Risk frequencies are from the Royal College of Obstetricians and Gynaecologists Consent Advice No. 2, Diagnostic Laparoscopy. The recommendation to operate laparoscopically wherever there is no contraindication, and to treat endometriosis found at the time of a diagnostic laparoscopy, follows NICE guideline NG73. Return-to-activity windows are typical post-operative ranges rather than guideline figures. This article is general information and does not replace advice from your own doctor.

Dr. Grishma Ranjangaonkar
MBBS, DGO · ICOG Fellowship in Gynecological Endoscopy · Maharashtra Medical Council Reg. No. 2014041327
Dr. Grishma has more than fifteen years of clinical experience and practises at Eva WomanCare Clinic in Vashi, seeing women from across Navi Mumbai including Kopar Khairane and Turbhe. Her work spans fertility and pregnancy care, PCOS and menstrual health, and keyhole gynecological surgery.
The full journey: preparing, the day itself, the shoulder pain nobody warns you about, and warning signs after discharge.
When heavy or painful periods are worth investigating, and what comes before surgery.
Why a polycystic-looking ovary on a scan is not a surgical problem.
If you are not yet sure whether what you have needs a same-day visit or a routine one.
If an operation has been advised and you are not sure it is the right one, or you want to understand what will be removed and what will be preserved, that conversation belongs before the date is booked. Bring your scans and reports.